
Why a comparative take actually helps
Hospitals and clinics don’t need another press release dressed up as a “solution”; they need straightforward choices that match patient flows and staff skills. That’s where a brisk, critical comparison becomes useful — and yes, the noisy gadget in the corner labeled as a cpap device is not the same animal as the auto‑adjusting systems you want on a ward. Global estimates place obstructive sleep apnea and related disorders in the hundreds of millions — roughly one billion adults at risk — so the stakes here are not hypothetical.

Key device categories and what they actually do
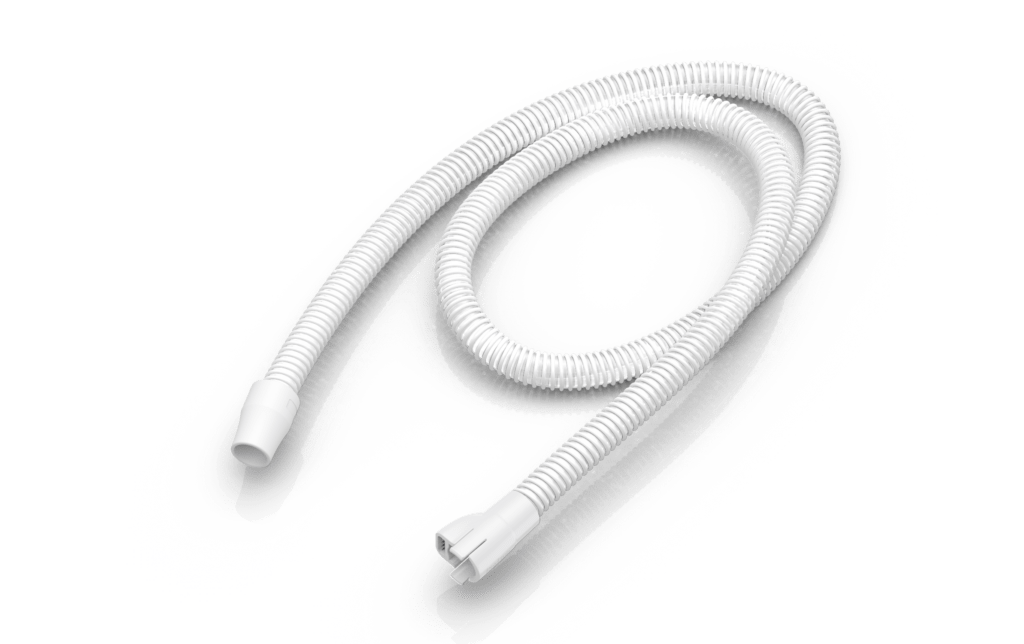
Reality: devices fall into categories because physiology demands it. Simple CPAPs deliver fixed continuous pressure; bi‑level systems switch between higher and lower pressures for inhalation and exhalation; auto‑adjusting (APAP) units alter pressure breath‑by‑breath based on flow signals. Expect terms like pressure support, mask interface, and humidifier to appear in procurement specs — they are the small print that changes patient tolerance and staff workload.
Operational trade‑offs that get skipped in glossy brochures
Comparative insight matters at three levels: patient comfort, nurse time, and IT integration. Bi‑level devices ease exhalation effort for COPD overlap; APAPs limit clinician titration time but demand reliable algorithms and good mask seals. Compliance tracking is great — until it floods clinicians with noisy alerts. In our operational production teardown, we tracked {main_keyword} and {variation_keyword} across device logs to see what truly correlated with therapy hours. Spoiler: it wasn’t the fanciest UI.
Common mistakes clinics make — blunt and brief
They buy the most bells and whistles under budget pressure and assume nurses will adopt. They ignore the mask interface inventory. They expect a single device to serve both acute ventilatory failure and long‑term sleep therapy. — Staff turnover makes “advanced settings” a liability if there’s no rapid on‑ramp training.
How to judge devices: practical comparison criteria
Compare devices on these concrete axes: responsiveness of auto‑adjusting pressure algorithms, ease of cleaning and disinfection of the mask interface, and the clarity of compliance reporting for respiratory therapists. Consider which units offer local data export versus cloud telemetry — the latter can be handy, but only if your IT team accepts medical‑grade integration requirements.
When APAP or Bi‑Level is the right pick
On sleep clinics and step‑down wards, an apap machine often wins for mixed populations because it tailors pressure without constant manual retitration. In respiratory wards handling acute hypercapnia, bi‑level or ventilator modes provide pressure support and backup rates not found in simple APAPs. Match device mode to clinical objective, not marketing copy.
Three golden rules for procurement (your quick checklist)
1) Measure the total staff time impact: include setup, daily checks, mask swaps, and data reviews. Devices that cut titration time but double data queries are a net loss. 2) Prioritize mask and interface logistics: invest in compatible mask sizes and clear cleaning protocols; patient tolerance improves measurable compliance. 3) Demand evidence of algorithm performance under variable leak conditions — a robust auto‑adjusting pressure algorithm must work when patients move or when the mask slips.
These are not trendy guidelines; they are what saves hours and prevents therapy failures in real wards. For hospitals aiming to deploy tailored auto‑ventilation across departments, thoughtful selection and local training are the real differentiators, and that’s where sensible partners come in. Byond. —

